Teresa’s TCM Clinical Reflections (23)
A Common Cause of Heel Pain — Plantar Fasciitis
By Teresa Shen, BHSc (Acupuncture), ACC Registered Treatment Provider, Registered Chinese Medicine Practitioner (NZ)
Heel pain is a very common problem in clinical practice, and plantar fasciitis is one of its common causes. Some patients have been in pain for several months, while others have experienced recurring symptoms for one or two years. The pain improves after a period of rest, but returns when they walk more or increase their exercise.
Some patients have already tried physiotherapy, stretching or shockwave therapy. Others have taken pain medication or received local injections, but the heel pain continues to return.
For some people, plantar fasciitis can be a persistent problem. However, when I see a patient with heel pain, my first question is still not how to treat it. I first want to know:
Is this really a plantar fascia problem?
What Kind of Heel Pain Suggests Plantar Fasciitis?
One characteristic feature of plantar fasciitis is pain with the first few steps in the morning.
Patients often tell me, “The first step when I get out of bed is the worst. After I walk for a while, it loosens up.”
A similar pattern can occur after sitting for a long time and then standing again. The pain may ease once the patient gets moving, but if they spend too long standing, walking or exercising, it can return later in the day.
On examination, typical tenderness is often found around the medial heel, near where the plantar fascia attaches to the calcaneus.
When these features come together, I am more likely to consider the plantar fascia as the source of the symptoms.
Heel Fat Pad Problems Can Look Different
There is a layer of fatty tissue underneath the heel that provides cushioning and protection. Problems involving the heel fat pad can also cause heel pain.
However, this pain is often more concentrated in the centre of the heel where it directly contacts the ground. The longer the patient stands or walks, the more noticeable it may become. Some patients feel worse in the afternoon or evening than in the morning.
Typical plantar fasciitis, by comparison, often has a characteristic pattern of pain when weight-bearing starts again after rest, particularly with the first steps in the morning.
That is why I often ask one simple question:
“When does it hurt the most?”
Sometimes a very simple question provides an important clue for differential diagnosis.
Numbness or Burning Makes Me Think About Nerves
Some heel pain is actually related to nerves.
If the pain is accompanied by numbness, burning, pins and needles, or a difference in skin sensation between the two heels, I do not examine only the plantar fascia.
There are several sensory nerve branches around the heel. Irritation or entrapment along a nerve pathway can also produce pain in this area. I therefore compare sensation on both sides, looking for reduced or increased sensitivity, and may examine further along the relevant nerve pathway according to the distribution of the symptoms.
Pain in the heel does not necessarily mean the plantar fascia is the problem.
A Heel Spur on X-ray Does Not Mean the Spur Is Causing the Pain
X-rays in middle-aged and older patients sometimes show a calcaneal or heel spur.
It is very easy for a patient to think, “That spur must be why my heel hurts.”
Clinically, it is not always that simple. Some people have obvious heel spurs on imaging but no heel pain. Others have significant heel pain, but the spur seen on X-ray may not adequately explain their symptoms.
I therefore consider the patient’s age, location of pain, tenderness, response to weight-bearing and imaging findings together.
Finding a structural change on imaging does not automatically mean we have found the source of the pain.
The absence of a fall or obvious injury also does not completely exclude a bone problem. A calcaneal stress injury or stress fracture, for example, may develop without one clear traumatic event. If weight-bearing pain is progressively worsening and there is focal bony tenderness, further investigation may be appropriate.
Before treatment, I therefore want to establish:
Is this actually a plantar fascia problem?
Why Can Plantar Fasciitis Keep Coming Back?
The plantar fascia repeatedly takes load and tension during everyday standing and walking. In long-standing plantar fascia problems, the condition is not simply a matter of “inflammation”. Repetitive loading may also be associated with micro-injury, tissue degeneration and changes in the repair process.
This can help explain why some patients improve when they rest, only for the pain to return once they resume prolonged walking, standing or exercise.
Pain medication may help control symptoms, while stretching, load modification and rehabilitation exercises are commonly used conservative approaches. Some persistent cases are also treated with shockwave therapy or local injections.
In clinical practice, however, I also see patients whose heel pain continues to recur despite trying several different treatments.
What I Have Learned from Treating Persistent Plantar Fasciitis
Over the years, I have used TCM pattern-based point selection, local acupuncture and channel-based distal points when treating plantar fasciitis. These approaches can help some patients, but for certain people with long-standing symptoms that repeatedly return after walking or exercise, I have found that conventional acupuncture alone is sometimes not enough.
Gradually, I developed my own approach for selected patients.
Once I am satisfied with the diagnosis, I carefully examine the plantar fascia to locate the clearest and most sensitive area of tenderness. Even when two patients have the same diagnosis of plantar fasciitis, the main area involved is not necessarily identical.
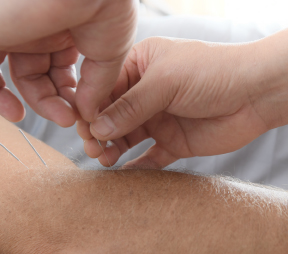
In treatment, I use Zhaohai (KI6) together with the main tender area identified during examination as important reference points. Depending on the individual presentation, I may use a more targeted through-needling technique so that the treatment is directed towards the area identified clinically.
For some patients with long-standing symptoms, when their general health and local tissue condition are suitable, I may also adjust the amount of mechanical stimulation used during needling.
But stronger stimulation is not automatically better. Age, general health, underlying medical conditions, local tissue condition and the patient’s tolerance all need to be considered.
What matters most is not which needle is used, but whether this approach is appropriate for this particular patient.
My aim is also not simply to make the heel feel temporarily less painful immediately after acupuncture.
For persistent plantar fascia problems, my clinical approach is to apply more focused mechanical stimulation to the main symptomatic tissue area, with the intention of encouraging a renewed local repair response.
This is an approach that has gradually developed through my years of clinical practice. I do not believe that all of its underlying tissue mechanisms can currently be explained by one simple process.
In practice, some patients show a clear reduction in first-step morning pain, local tenderness and walking pain after several treatments, while others may maintain improvement for a longer period. However, every patient’s history, tissue condition and response to treatment are different, so the same number of treatments cannot be expected for everyone.
After treatment, I reassess the original tender area and ask the patient to repeat the weight-bearing movement that previously reproduced the symptoms.
TCM Treatment Still Requires Pattern Differentiation
Even when two patients both have plantar fasciitis, their Chinese medicine treatment does not necessarily need to be identical.
If the heel feels cold, heavy and achy, with symptoms aggravated by cold conditions, I may consider a Cold-Damp obstruction pattern and, where appropriate, combine acupuncture with moxibustion to warm and promote circulation through the channels.
For long-standing, relatively fixed pain with marked local tenderness, the TCM pattern may be more consistent with Qi Stagnation, Blood Stasis and obstruction of the channels, leading to a treatment approach focused more on promoting circulation and restoring the free flow of Qi and Blood.
So my treatment of plantar fasciitis is not based on one special needling technique alone.
Modern clinical assessment helps me decide whether the plantar fascia is actually the problem. TCM channel theory and pattern differentiation help me decide how to treat the individual patient.
First identify the cause of the heel pain, then choose the approach that suits the patient. This is one of the most important lessons I have learned from treating plantar fasciitis.
Related Articles
Teresa’s TCM Clinical Reflections | Traditional Chinese Medicine Perspectives on Health, Recovery and Healing
All Teresa’s TCM Clinical Reflections
Teresa’s Case Study (1) | Why Did Persistent Ankle Swelling Improve So Much After One Treatment?
Teresa’s TCM Clinical Reflections (23) A Common Cause of Heel Pain — Plantar Fasciitis
Book an Appointment
If your heel is particularly painful with the first steps in the morning, hurts again after sitting for a long time, or has continued to affect walking or exercise for several months, a clinical assessment may help determine whether the plantar fascia is actually the source of the pain or whether another heel problem should be considered.
Treatment is selected according to the clinical findings, duration of symptoms and individual patient rather than using the same approach for every case of heel pain.
https://booking.mananotes.co.nz/PHD-WIN/v2
Disclaimer
This article is provided for general health education and shares Teresa Shen’s clinical observations and treatment approach. It does not provide an individual diagnosis or replace appropriate medical assessment.
Heel pain has many possible causes besides plantar fasciitis. Persistent or worsening pain, inability to bear weight, focal bony tenderness, neurological symptoms or an atypical clinical presentation may require further medical assessment or imaging.
The acupuncture, through-needling and moxibustion approaches discussed in this article are examples of clinical treatment considerations. The appropriate technique and level of stimulation need to be determined individually by a suitably qualified registered practitioner.



 中文微信:nzacupunctureclinic


Leave a reply