
Once clinicians form an initial diagnosis, it is natural to notice evidence that supports it. But some of the most valuable clinical clues are the findings that do not fit. A shoulder pain case prompted Dr Win Huang to reflect on diagnostic closure, contradictory evidence and the importance of challenging our own clinical framework.
> View article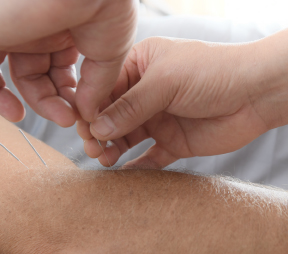
Follow Dr Win Huang through real clinical cases and see how the patient’s history, pain pattern, physical findings and response to treatment are brought together. This series focuses not on fixed treatment formulas, but on the clinical reasoning behind assessment and treatment decisions.
> View article
Doctors and patients ultimately want the same thing: improvement. But they may understand disease, recovery, testing and treatment very differently. Good clinical care requires both professional integrity and meaningful patient participation.
> View article
After years of independent practice, almost every clinician develops a personal clinical framework. The challenge for an experienced doctor is not simply to build that framework, but to recognise its limitations and remain open to evidence outside it.
> View article
A young patient came expecting cervical manipulation after an X-ray suggested a neck problem. Re-examination pointed instead toward ulnar nerve irritation at the elbow—a reminder that treatment should follow assessment, not labels.
> View article
Patients bring symptoms, not diagnoses. Good clinical reasoning means turning those symptoms into clues, forming hypotheses, testing them through history and examination, ruling out alternatives and continually reassessing the evidence.
> View article
When pain disappears after one treatment, the result may be genuine—but what does it actually prove? Dr Win Huang reflects on immediate treatment responses, clinical reasoning and why doctors must distinguish real outcomes from explanations that go beyond the evidence.
> View article
A diagnosis is rarely found by chance. Experienced clinicians follow clues, develop diagnostic hypotheses, test them through history taking and examination, and gradually narrow down the possibilities. Dr Huang shares the clinical thinking developed over more than forty years in practice.
> View article
The patient arrived with a diagnosis already in mind: BPPV. He had researched extensively, consulted doctors, watched videos, and even asked AI. Yet after careful assessment, Dr Huang concluded it was unlikely to be BPPV. This case explores why saying “No” is sometimes one of the most important responsibilities of a clinician.
> View article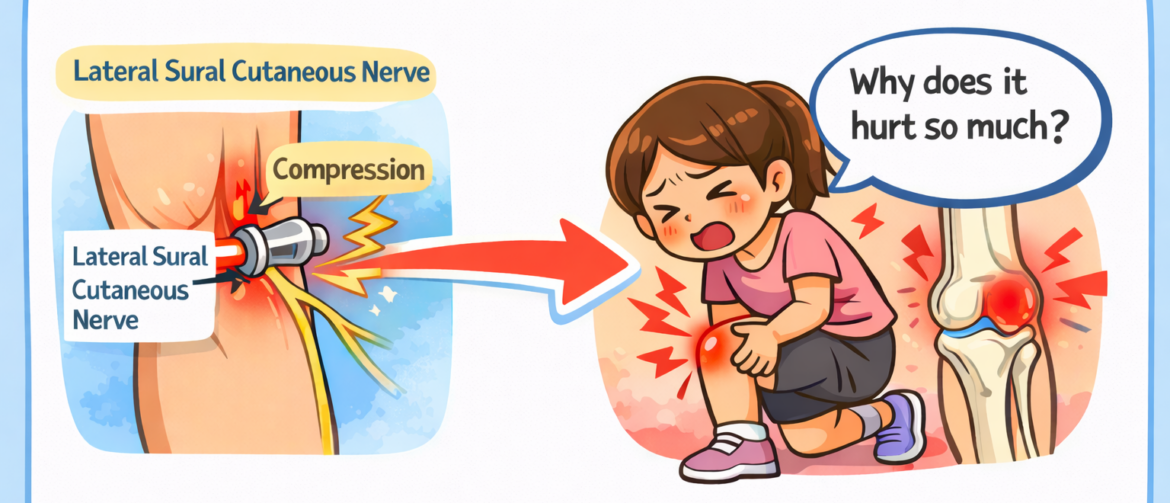
I used three-edged needle pricking with mild bloodletting, followed by localized cupping, aiming to release fascial tension in this region.
The result was immediate.
> View article


 中文微信:nzacupunctureclinic

